
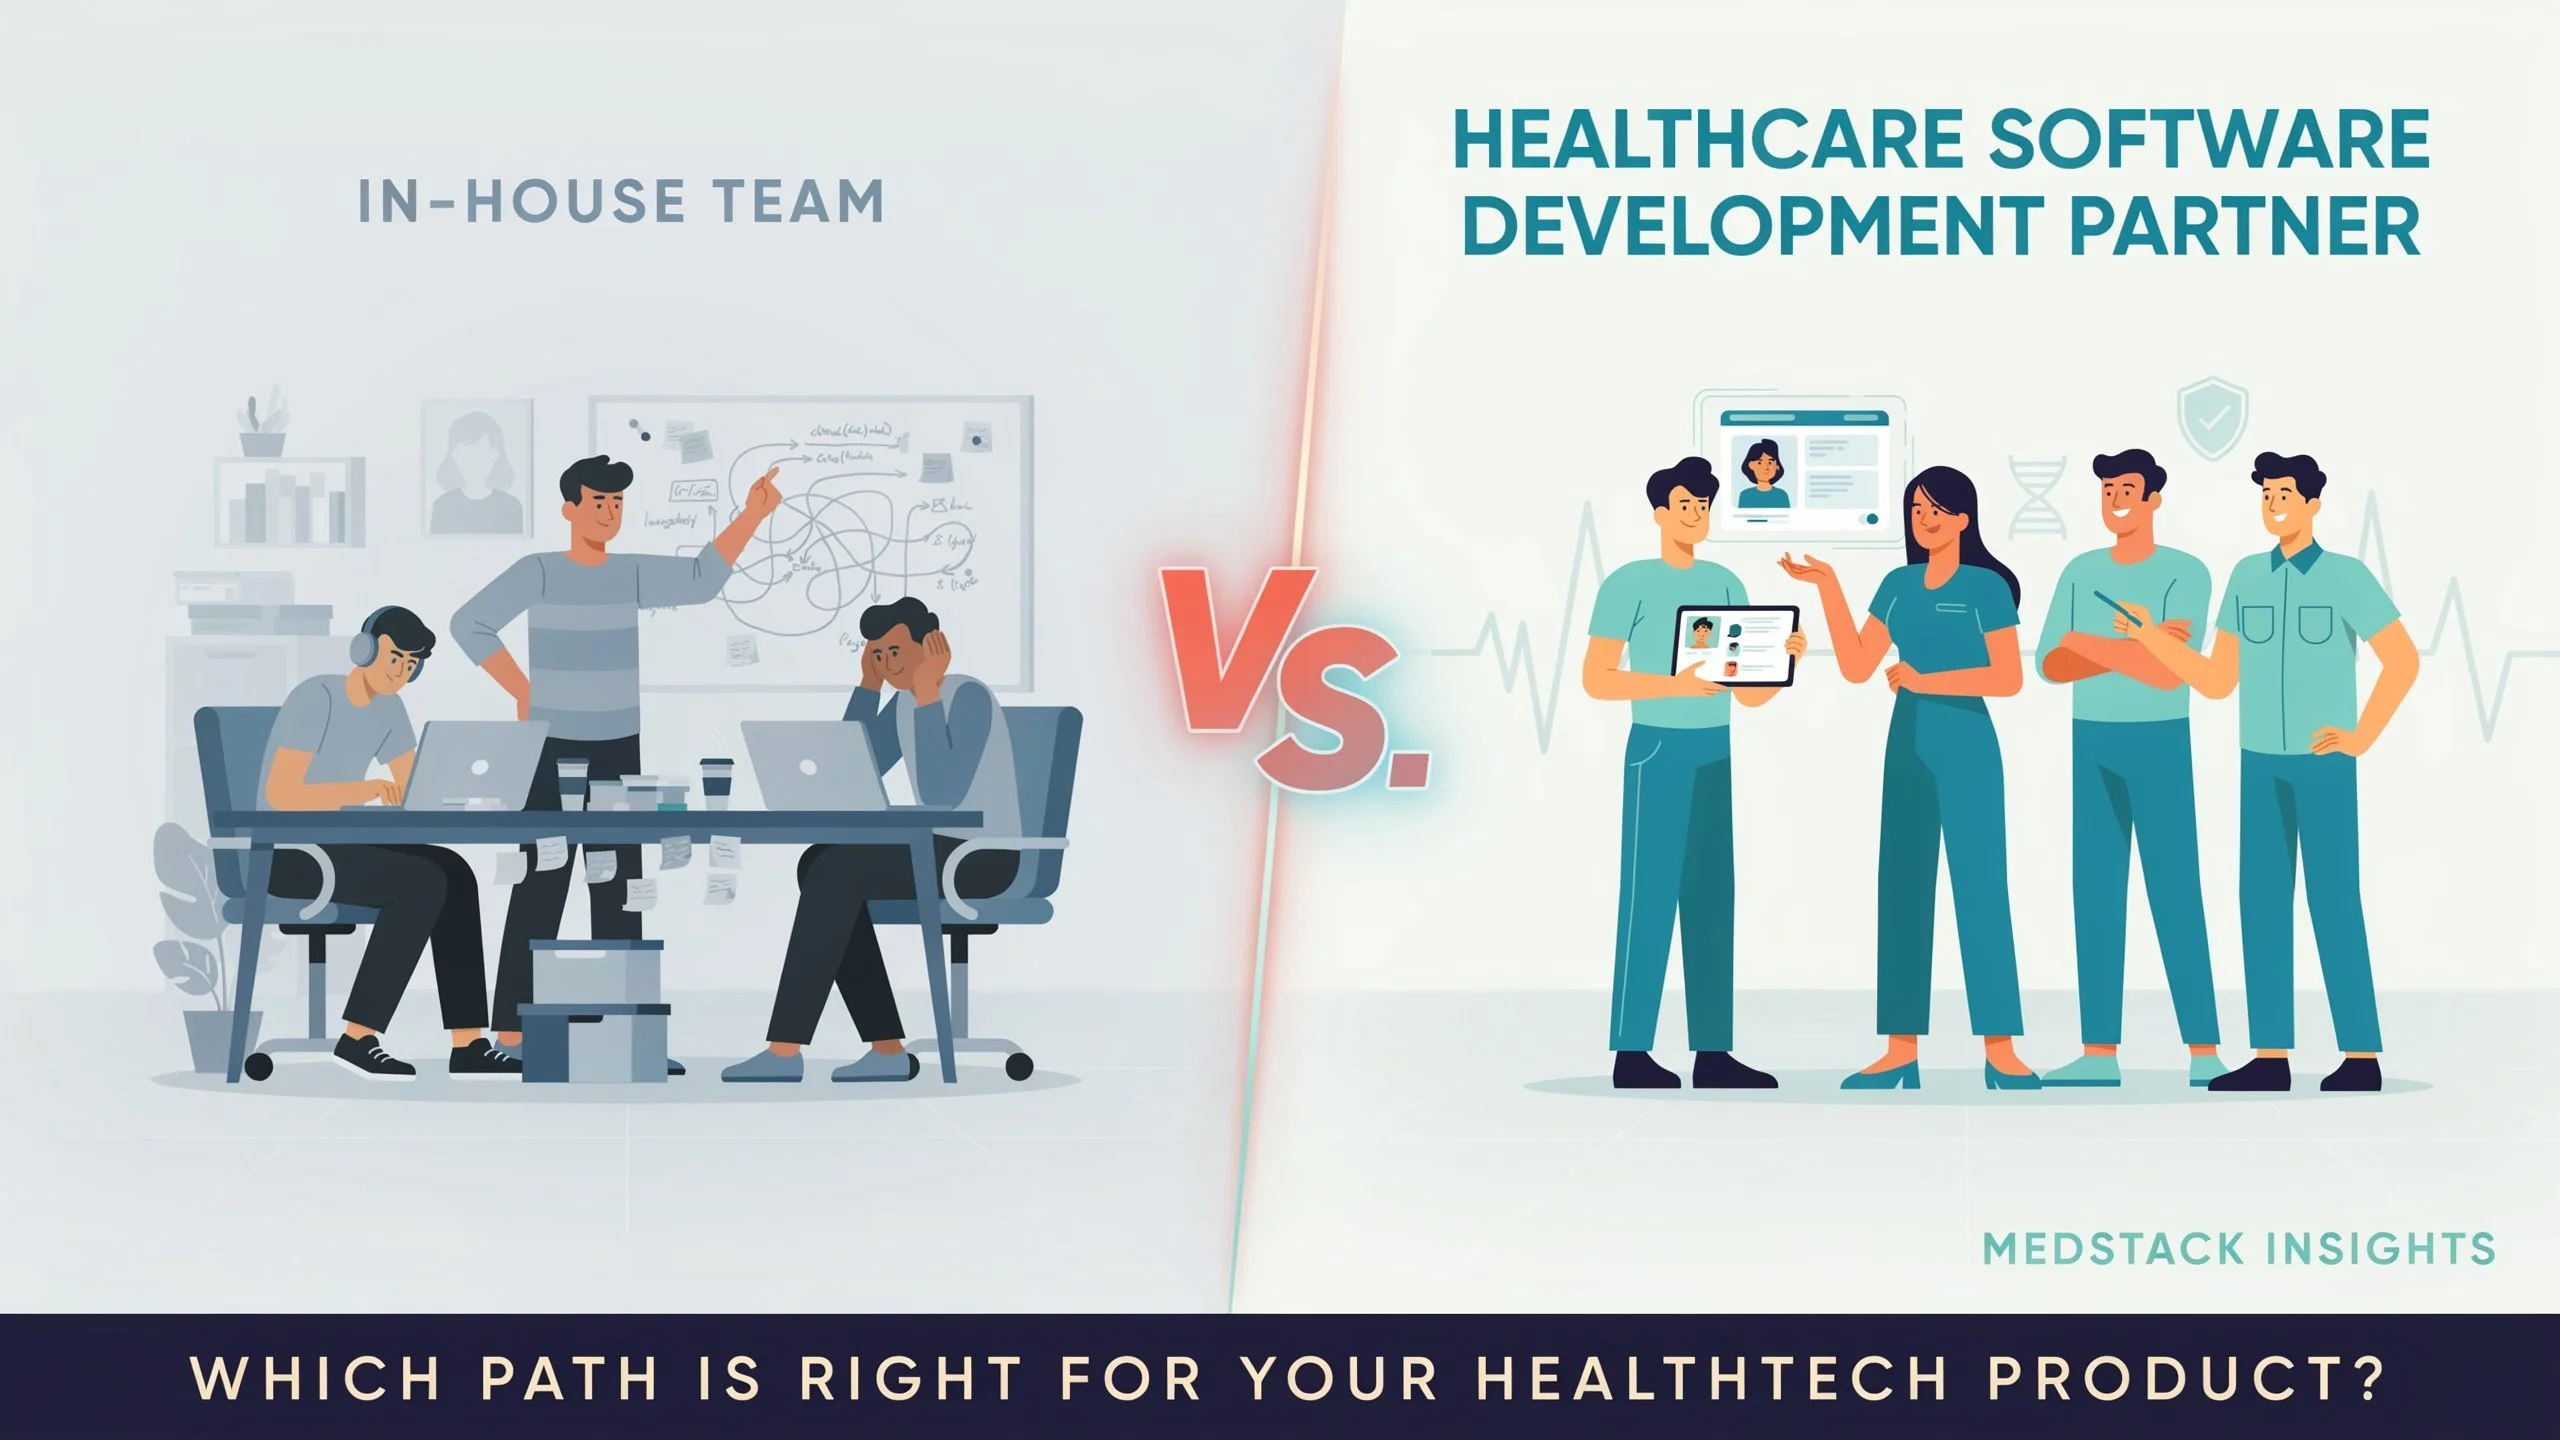
Every founder building a healthcare product hits this fork: hire your own engineers, or work with a partner who builds it for you. Both can work. They fail in different ways, and the right call depends on where you are, not on which one sounds more impressive.
I'll give you the honest version, including when a partner is the wrong choice.
Must Read: How to Choose a Healthcare Software Development Company
What hiring in-house really costs
The salary is the part everyone quotes. It's the smallest part. A good US senior developer runs well into six figures, then add recruiting time, benefits, equipment, and the two-to-three month ramp before they're productive.
There's a quieter cost too. One engineer is one point of failure. They get sick, take leave, or leave entirely, and your roadmap stops. So one hire becomes two, then a lead to manage them, and now you're running an engineering team. If you're a non-technical founder, you're also managing work you can't fully evaluate, which is its own kind of exposed.
In-house earns its keep when software is your core product and you're building for the long haul with the budget to staff a real team. Early on, before you've validated much, it's often the slow, expensive path.
What a partner really gets you
A healthcare software development partner gives you a team that already works together, with a senior who owns delivery, usually for less than one fully loaded in-house salary. In healthcare specifically, they bring something a fresh hire doesn't: they've handled protected health data before and know where the compliance landmines are.
The speed difference is real. There's no hiring cycle and no ramp. The team starts.
Where a partner goes wrong
This is the part most agencies won't tell you. A partner is the wrong choice if you pick the cheap one. A low quote usually means juniors with no senior oversight, and you pay for that in a rebuild. It's also wrong if the partner won't commit to fixed scope, won't put a named senior on your work, or can't show healthcare experience. And if your product is so core and long-term that you genuinely need deep in-house ownership, a partner is a bridge, not the destination.
The way to avoid the bad version is to vet properly, which we walk through in how to choose a healthcare software development company.
A simple way to decide
Ask yourself two questions. Is software the core long-term product of my company, with the budget to staff it well? And do I need to move now, with limited tolerance for hiring delays and early mistakes?
If you need speed and senior judgment without building an org chart, a partner fits. If you're staffing a long-term product team and can absorb the ramp, in-house makes sense. Plenty of founders start with a partner to ship and validate, then build in-house once there's something proven to build around.
If you're trying to make this call for your own product, send us the details and we'll tell you straight which way we'd lean, even if the answer is in-house.
Must Read: How Much Does It Cost to Build a Healthcare App in 2026?
Blogs:
Explore all blog
HL7 Integration Services: What You're Actually Paying For
A CTO told us his platform was FHIR-native, so HL7 wasn't his problem. Two weeks later the hospital sent over a spec for an ADT feed over MLLP. Here's what HL7 integration work actually involves, and what makes one interface cost three times another.
Clinical Data Integration: Why the Single Patient View Is So Hard to Build
A team demoed a beautiful unified patient dashboard. A nurse in the room asked one question: is this medication list current? Nobody could answer it. That question is the whole problem with clinical data integration.
EMR vs EHR: The Two Acronyms Quietly Confusing Your Healthcare Build
A founder once lowered his voice on a call and asked, like he was confessing something: "What's actually the difference between an EMR and an EHR?" Six months into building a healthtech product. Here's the answer, and why it changes your build.